Modern Technology Behind Dental Implants in Calabasas CA
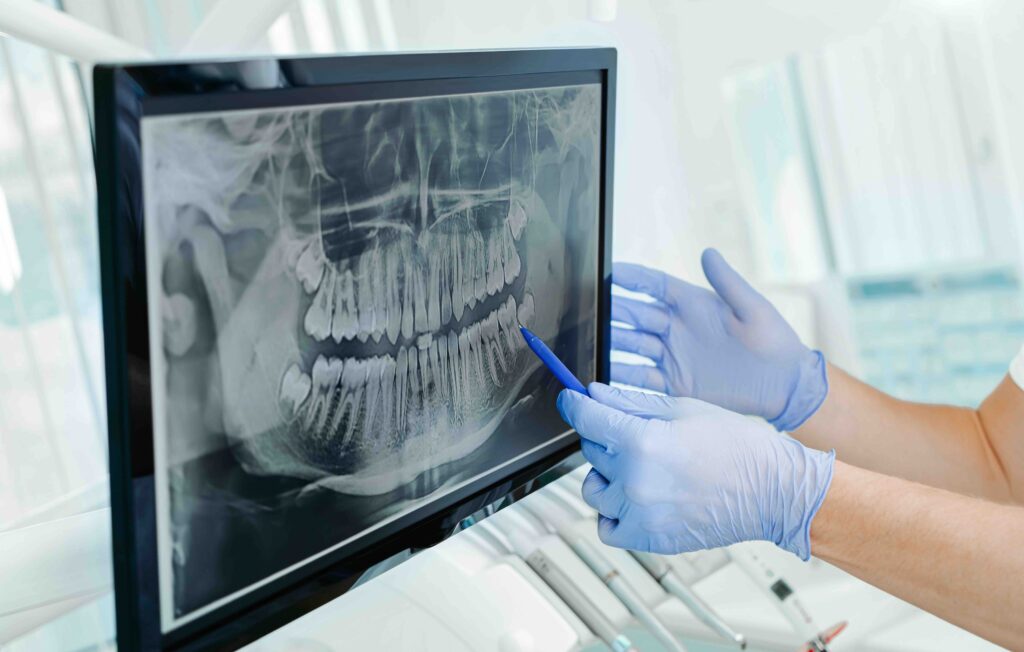
A dental implant may look simple once the crown is in place, but the process behind it is anything but basic. What patients see is a natural-looking tooth replacement. What clinicians see is a blend of imaging, digital planning, biomaterials, surgical precision, and healing biology that has improved dramatically over the past decade.
That matters in a place like Calabasas, where patients often arrive with high expectations and complex histories. Some want a single front tooth replaced with flawless esthetics. Others have worn a partial denture for years and are tired of movement, sore spots, and compromised chewing. Many are balancing cosmetic goals with practical concerns such as recovery time, long-term durability, and whether enough bone remains to support an implant at all.
Modern implant dentistry is no longer just about placing a titanium post into the jaw and hoping it integrates well. The strongest outcomes come from a carefully staged digital workflow, thoughtful case selection, and technology that reduces guesswork. When people search for Dental Implants Calabasas CA, they are often really asking a deeper question: what makes one implant experience more predictable, comfortable, and natural than another?
The answer starts long before surgery.
The shift from estimation to precision
Years ago, implant placement relied heavily on two-dimensional X-rays, physical models, and the clinician’s spatial judgment at the chair. Skilled dentists achieved good results, but limitations were real. A standard film could show height, yet it could not reliably reveal the true width of bone, the angulation of a ridge, or the exact relationship between an implant site and nearby anatomy such as the sinus or the inferior alveolar nerve.
Modern technology changed that. Today, planning an implant case often begins with three-dimensional imaging and digital records that let the restorative plan drive the surgical plan, not the other way around. That distinction is easy to miss, but it is central to quality treatment. The implant should be placed where the final tooth needs support, not merely where bone seems available at first glance.
In practice, this means the dentist can evaluate bone dimensions more accurately, identify defects earlier, anticipate grafting needs, and choose implant size and angulation with far more confidence. For patients, better planning usually translates into fewer surprises during surgery and a stronger chance of a stable, esthetic result.
Cone beam CT scanning and why it matters
One of the most influential tools in implant dentistry is cone beam computed tomography, often shortened to CBCT. Unlike a conventional dental X-ray, a CBCT scan captures a three-dimensional view of the jaw, teeth, and surrounding structures. It allows the clinician to assess width, height, density patterns, sinus anatomy, root positions, and nerve pathways in a way that flat images simply cannot.
This is especially valuable in situations that look straightforward but are not. A missing lower molar may appear to have plenty of room, yet the nerve canal might run close to the crest of bone. A front tooth lost years ago may leave a ridge that appears normal from the front but is actually thin from lip to palate. Patients who were told elsewhere that they are not candidates for implants sometimes turn out to be treatable after proper 3D evaluation, while others benefit from learning early that bone grafting or staged treatment will be necessary.
CBCT also improves communication. A patient can look at the scan and understand the reason for a graft, the need for sinus elevation, or the value of a narrower implant in a restricted site. That shared understanding tends to reduce anxiety because the plan feels grounded in visible anatomy rather than vague explanation.
Radiation exposure is a common concern, and it is a fair one. A CBCT scan does involve more radiation than a single small dental X-ray, though the amount varies widely depending on the machine and settings. Good practices use the smallest field of view and lowest effective dose that still delivers the information needed. The goal is not to scan everyone reflexively. The goal is to scan when the information meaningfully improves treatment planning and safety.
Digital impressions and the end of the goopy tray for many cases
Traditional impressions had their place, but patients rarely miss them. Anyone who has struggled with a bulky tray of impression material pressing against the palate understands why digital scanners gained traction so quickly.
An intraoral scanner captures a detailed digital model of the teeth and soft tissues. For implant dentistry, this is useful before treatment and after implant placement. Before surgery, it helps document the bite, neighboring tooth contours, and the soft tissue architecture that will influence the final restoration. After integration, it may be used to capture the implant position through a scan body, allowing a crown or bridge to be designed with impressive precision.
The practical benefit is not just comfort. Digital impressions can improve workflow accuracy and speed. Laboratories receive a clean file instead of a stone model that could chip or distort. The restorative dentist can evaluate contact points, emergence profile, and esthetic contours in software before the final crown is milled or layered.
Still, technology does not erase technique sensitivity. Edentulous arches, deep subgingival margins, mobile tissue, and limited mouth opening can challenge scanners. There are cases where a conventional impression remains the better choice. Experienced implant dentists know when to lean on digital systems and when not to force them.
Virtual implant planning makes the prosthetic result the priority
The most refined implant cases begin with the end in mind. Virtual planning software allows the clinician to merge CBCT data with digital surface scans, creating a composite model of bone, teeth, and soft tissue. With that merged view, the implant can be positioned according to the future restoration rather than bone anatomy alone.
For example, a front tooth implant that is placed a few millimeters too far toward the lip may look acceptable on a radiograph yet create a long crown, gray shine-through, or gum recession months later. A posterior implant set at the wrong angle might force the restorative dentist to use a compromised crown contour that traps food and becomes difficult to clean. These are not minor issues. They affect esthetics, hygiene, patient satisfaction, and the lifespan of the work.
Virtual planning helps reduce those risks by letting the team assess:
- implant diameter and length relative to available bone
- angulation in relation to adjacent roots or implants
- restorative space for the abutment and crown
- screw access position in screw-retained restorations
- whether grafting or soft tissue enhancement should be done at the same stage
For a patient, this planning often feels invisible. It happens on a screen before the appointment. Yet it can be the difference between a straightforward restoration and a cascade of compromises.
Surgical guides and the role of guided implant placement
Once a digital plan is approved, a surgical guide can often be fabricated. This is a custom template, usually made from resin, that fits over the teeth, gums, or both and directs the drill sequence Dental Implants Calabasas CA Oaks Dental according to the planned implant position.
Guided surgery is not magic, and it is not required in every case. A very experienced surgeon may freehand a simple posterior implant with excellent control. But guided systems are valuable when precision matters most, especially around limited bone, esthetic zones, full-arch reconstructions, or cases where several implants must align with a predesigned prosthesis.
What patients often notice is efficiency. A well-made guide can shorten surgical time and reduce hesitation during the procedure. In selected cases, the surgery is less invasive because the clinician can work through a smaller access point rather than reflecting a large flap. That may mean less swelling afterward, though recovery still depends on the individual case, bone quality, and whether grafting was performed.
There is a trade-off. Guided surgery depends on accurate data capture, correct guide fabrication, and proper seating in the mouth. Errors can stack. If the scan is flawed, the merge is off, or the guide rocks slightly during use, precision suffers. Technology improves predictability, but only when the operator respects its limits and verifies every step.
Implant surfaces and the biology of integration
Patients often hear that an implant is made of titanium, but the material story is more nuanced than that. The surface of the implant plays a major role in osseointegration, the biological process in which bone bonds to the implant. Manufacturers use different surface treatments to increase microscopic roughness or alter surface chemistry in ways that encourage faster and stronger bone response.
This is one reason implant treatment timelines have evolved. Years ago, extended healing periods were common before loading the implant. Today, depending on primary stability, bone quality, bite forces, and the location of the implant, some cases allow earlier restoration than was once routine. Immediate placement and immediate provisionalization are even possible in carefully selected situations, particularly in the front of the mouth where preserving soft tissue contours is a high priority.
That said, biology still sets the rules. A patient with excellent bone and no parafunctional habits may support a more accelerated timeline. Someone who grinds heavily, smokes, has uncontrolled diabetes, or has significant bone loss may need a slower, more protected course. The technology improves the odds, but it does not repeal healing physiology.
Zirconia, titanium, and material choices patients ask about
Titanium remains the standard for most implants because it has a long track record and excellent biocompatibility. It is strong, versatile, and supported by decades of clinical use. Zirconia implants attract interest from patients who want a metal-free option or who are concerned about esthetics in very thin tissue. In certain cases, zirconia can be considered, but it is not a universal replacement for titanium.
The real-world question is not which material sounds more modern. It is which material best fits the site, the restorative plan, the patient’s bite forces, and the available evidence. Titanium still carries the broader base of long-term data, especially in complex and full-arch applications. Zirconia may be useful in select cases, though its prosthetic flexibility can be more limited depending on the system.
Restorative materials matter too. The final crown may be layered ceramic, monolithic zirconia, or another material chosen based on esthetics, strength, and the location in the mouth. A front tooth often prioritizes translucency and gum harmony. A second molar usually prioritizes durability under load. Good implant dentistry is full of these judgment calls.
Bone grafting has become more refined and more predictable
One of the biggest misconceptions around implants is that lack of bone means the conversation is over. In many cases, modern grafting techniques make treatment possible even after years of tooth loss. Extraction sockets can be preserved at the time of tooth removal. Localized defects can be rebuilt with particulate grafts and membranes. The upper back jaw may be improved through sinus augmentation when vertical bone is limited.
Technology supports these procedures in several ways. CBCT imaging identifies the shape and severity of the defect. Digital planning helps decide whether grafting should happen before implant placement, at the same time, or not at all. Improved membranes, fixation methods, and biomaterials have expanded what can be predictably managed.
None of this means every deficient site should be pushed toward treatment. Sometimes the grafting burden outweighs the benefit, particularly in medically complex patients or when a more conservative prosthetic solution would serve the patient better. Experienced clinicians are honest about that. The presence of advanced tools should not tempt anyone into overtreatment.
Soft tissue technology is often the hidden difference between an average result and a beautiful one
Patients tend to focus on the implant itself, but the gum tissue around it often determines whether the restoration looks natural. In the esthetic zone, even a well-integrated implant can look artificial if the tissue contour is flat, asymmetric, or thin enough to show a gray undertone.
Modern implant care pays far more attention to digital smile design, tissue management, provisional shaping, and custom healing components than in the past. Temporary restorations can be used strategically to sculpt the soft tissue before the final crown is delivered. Custom abutments can support the gum in a more anatomically appropriate way. Digital design helps mirror the contralateral tooth and maintain papilla form where possible.
This is the part of implant dentistry patients rarely see in online before-and-after photos. The best front tooth cases may involve several refinements over weeks or months, especially if the tooth was lost due to trauma, infection, or severe fracture. The technology helps, but patience and tissue judgment still make the result.
Same-day teeth, immediate implants, and what those terms really mean
Marketing around implants can be confusing. Phrases like “same-day implants” or “teeth in a day” can refer to different treatment models, and patients deserve clarity before they commit.
In some cases, a failing tooth can be removed and an implant placed during the same appointment. In a narrower set of cases, a temporary crown may be attached right away. Full-arch treatment may allow a patient to leave surgery with a fixed provisional bridge supported by implants placed that day. These are real possibilities, but they are not automatic.
Whether immediate treatment is wise depends on several factors:
- the quality and quantity of bone available for initial stability
- whether active infection has compromised the site
- the amount of biting force the temporary restoration will face
- the patient’s ability to follow a restricted diet during healing
- esthetic demands and soft tissue conditions
A patient who clenches heavily or cannot realistically protect the temporary restoration may be a poor candidate for immediate loading, even if the surgery itself goes well. There is no prize for rushing a timeline that should have been staged.
How technology improves comfort, not just accuracy
Most patients judge implant treatment by a simpler standard than clinicians do. They want to know whether it will hurt, how long they will be out of commission, and whether they can get back to work quickly. Modern technology helps here too, though perhaps less dramatically than marketing suggests.
Precise planning can shorten procedure time. Guided placement may reduce tissue trauma in selected cases. Better temporary restorations mean fewer emergency visits for ill-fitting flippers or loose acrylic teeth. Digital communication with the lab can cut remake rates. Medication protocols and local anesthesia techniques have improved, and many offices can coordinate oral sedation or IV sedation when appropriate.
From experience, patient comfort often comes down to the small operational details. A surgical visit that starts on time, moves efficiently, and includes clear post-op instructions tends to feel easier than one that is technically competent but disorganized. High-tech equipment matters, but so does the human system around it.
Maintenance technology matters after the implant is placed
An implant is not maintenance-free. That point deserves emphasis because many failures are not surgical failures at all. They are maintenance failures, bite-related problems, or inflammatory issues that build quietly around an otherwise well-placed implant.
Modern follow-up care often includes digital radiographic monitoring, occlusal evaluation, professional hygiene protocols designed for implants, and in some offices, tools that help assess inflammation or plaque retention patterns. The goal is to catch peri-implant mucositis before it becomes peri-implantitis, and to identify bite overload before screws loosen or restorative components fracture.
Patients in Calabasas who invest in implants often expect them to last decades. Many do. The best chance of that outcome comes when the restoration is cleaned properly, the bite is monitored over time, and risk factors such as smoking, dry mouth, or nighttime clenching are addressed early.
What patients should ask when evaluating implant care
The technology behind modern implant treatment is impressive, but equipment alone does not guarantee good care. Two offices may both advertise advanced imaging and digital workflows while delivering very different experiences and outcomes.
A useful consultation usually includes a discussion of diagnosis, alternatives, timing, risks, and maintenance, not just a fee quote. Patients considering Dental Implants Calabasas CA should feel comfortable asking how the implant position will be planned, whether 3D imaging is recommended for their case, who is designing the final restoration, and what contingencies exist if grafting or additional treatment is needed.
They should also listen for honesty. If a clinician explains where technology helps and where biology still imposes limits, that is a good sign. If every case is framed as easy, instant, or universally suitable for same-day treatment, skepticism is healthy.
Where all of this is heading
Implant dentistry continues to move toward better integration between diagnostics, surgery, and restoration. The gap between planning and execution is narrowing. Scans, software, printed guides, custom abutments, and digitally milled restorations now work together in a way that was far less coordinated not long ago.
Yet the most meaningful progress is not flashy. It is the steady reduction of avoidable error. It is being able to preserve tissue more predictably, place implants more prosthetically, and restore them with fewer compromises. It is recognizing the patient who should have immediate treatment and the patient who will do better with a staged plan. It is using technology to support judgment, not replace it.
That is what modern implant care should feel like in practice. Not futuristic for its own sake, but precise, measured, and tailored to the person in the chair. For patients exploring options for tooth replacement, that blend of digital accuracy and clinical restraint is often what turns a complex procedure into a durable, natural result.
Oaks Dental
5000 Parkway Calabasas, Suite 308
Calabasas, CA 91302, United States
Phone: +1 (818) 412-8349
FAQ About Dental Implants Calabasas CA
How much does a dental implant cost in California?
Costs vary with the number of teeth replaced, restoration type, imaging, and any extractions or bone grafting. Request an itemized estimate after an examination; a single advertised price may not include every treatment stage.
Can people with autoimmune disease get dental implants?
Some people may qualify, but the condition, medications, oral health, and healing risks require individual assessment. Share your medical history with your dentist, who may coordinate with your treating physician.
Can you have dental implants if you have osteopenia?
Osteopenia does not by itself establish whether implants are suitable. Your dentist must evaluate jawbone support and review bone-related medications and other risks before recommending treatment.
Corrections
Spot something wrong? Send it to the desk and it gets fixed in the open.